Thursday, 21 July 2016

Government undertakes Indoor residual spraying in 10 epidemic districts in northern Uganda

In a bid to intensify efforts towards the management of the malaria epidemic in northern Uganda, the Ministry of Health is undertaking indoor residual spraying (IRS) in 10 epidemic districts in September this year. The exercise is intended to contribute to the objective of achieving and sustaining protection of at least 85% of the most at risk population.
IRS is the application of a long-lasting residual insecticide to potential malaria vector resting surfaces such as walls, eaves and ceilings of all houses or structures, including domestic animal shelters.

The IRS will be conducted in districts of: Kitgum, Amuru, Agago, Apac, Gulu, Kole, Lamwo, Nwoya, Oyam and Pader. Approximately $9m (Shs 29.7b) has been earmarked for the activity, with funding support from government of Uganda USAID/Presidents Malaria Initiative and DFID.


WHY IRS @ THIS TIME


According to a recent Malaria Indicator Survey, IRS has rapidly reduced malaria outpatient attendances, in-patient case admissions and malaria test positivity rates in all districts where it has been implemented. Additionally, IRS controls other household pests such as bedbugs, houseflies, lice and fleas, making it cost effective and acceptable to the communities as they spend less on treatment of related diseases.
“The exercise is being undertaken with the background that malaria remains the biggest cause of morbidity and mortality in Uganda. It is therefore critical for its reduction and interruption of malaria transmission,” said Prof Anthony Mbonye in a press release.
Mbonye is the director general of health services in the ministry of Health.
The IRS is being used together with other malaria interventions such as use of long lasting insecticide treated nets, case management, intermittent preventive treatment in pregnancy (ITPp), surveillance and behavioral change communication.

The Ministry urges the public to destroy all breeding places for malaria vectors by slashing compounds; work closely with village health teams to monitor and report cases to health facilities; sleep under a treated bed net and for those already diagnosed with malaria to complete the dose of anti-malarials given to them.
According to the Uganda Malaria Reduction Strategy 2014-2020, it is hoped that by 2020 the country will have reduced annual malaria deaths to near zero and a reduced malaria morbidity to 30 cases per 1000 people.

Wednesday, 20 July 2016

Thousands flee to Uganda from South Sudan following latest violence

A refugee shows off some of the deceased relatives (Photo credit-Oxfam)


The number of people seeking shelter and safety in Uganda from South Sudan has risen significantly in the past few days and we believe the influx will keep growing in the days ahead as tensions remain high across the border.

A total of 1,326 crossed into Uganda between Friday and Saturday, with 1,633 more arriving on Sunday. The majority are South Sudanese, but there are also believed to be some Ugandans. Prior to Friday, the average daily rate was 233. These new arrivals bring the total number to have fled to Uganda since the latest violence in South Sudan began on July 7 to 5,015. More than 90 per cent of the new arrivals were women and children under the age of 18 years.

UNHCR expects more people to flee to Uganda, especially now that the 200-kilometre Juba-Nimule road, linking the South Sudan capital to Uganda, has been cleared of checkpoints. As a result, more people are now coming by truck, and this explains the rising numbers of arrivals. Many are also bringing belongings.
Thousands of people have entered Uganda’s northern region via the border crossing points at Moyo, Kuluba, Lamwo, Yumbe and Elegu, while some are heading directly to Kiryandongo refugee settlement in the mid-west of the country. The border was previously closed on the South Sudan side, but restrictions have been eased.
The new arrivals are mostly fleeing from Eastern Equatoria state, with a smaller number arriving from Juba. They report that the security situation remains volatile and fighting could return at any time. The refugees talk of an increase in looting.

Inside Uganda, more than 6,000 South Sudanese are staying in the Pagiarinya settlement in Adjumani District, while others are waiting at collection points to be transferred to the settlement. A recent evaluation found that Pagiarinya has capacity for another 6,500 people, meaning it is likely to be full within a few days.
An inter-agency site assessment mission, including officials from the Government of Uganda Office of the Prime Minister and UNHCR, are currently visiting sites to identify areas suitable for establishing new settlement areas.
People are arriving in Uganda tired and hungry. Many of them have walked for days carrying belongings. Others are suffering from malnutrition after walking without food for days. Militia activities in some areas of South Sudan have made it difficult to harvest crops in recent months.

Some of the refugee children queue for food-Photo credit-UNHCR


The UN has said that at least 300 people were killed and over 10,000 fled their homes after the violence in Juba. We condemn violent attacks against humanitarian workers, which have left at least one person dead. Several countries have evacuated their nationals. UNHCR, as part of the overall humanitarian response, is undertaking assessments and providing assistance in displacement sites.

Although a fragile ceasefire has held since late Monday, the United Nations has warned of the possibility of fresh fighting in Juba. The situation is being exacerbated by the devaluation of the South Sudanese pound, leading to skyrocketing prices and making the food that is available too expensive for many. The fighting also disrupted supply routes from Uganda into South Sudan, including aid and food.

In western Ethiopia’s Gambella region, the number of new arrivals has not risen significantly since June 11, but the fresh fighting has dampened hopes of returning home soon. The Kenya-South Sudan border has also been relatively quiet. To date UNHCR has transferred 169 new arrivals from the Nadapal border to Kakuma camp. 
The fresh displacement will put a further strain on UNHCR’s resources for the South Sudan operation and our ability to provide timely and life-saving assistance. Especially with access to Juba difficult. Last Friday in Nairobi, UNHCR presented a revised appeal for its South Sudanese refugees operations, seeking US$701 million. The earlier appeal for US$638 million was only 17 per cent funded.

Presenting the appeal, Ann Encontre, Regional Refugee Coordinator for the South Sudan situation, said the overall planning figure had risen from 867,239 refugees to 973,000. She warned that it could pass the 1 million mark in the coming months.

For more information on this topic, please contact:
In Kampala, Charles Yaxley, yaxley@unhcr.org , +256 (0) 776 720 045 
In Nairobi, Teresa Ongaro, ongaro@unhcr.org, +254 735 337 608
In Geneva, Leo Dobbs, dobbs@unhcr.org +41 79 883 6347
In Nairobi, Duke Mwancha, mwancha@unhcr.org +254 722 207 863

Monday, 18 July 2016

PRESS STATEMENT ON THE UGANDA POPULATION BASED HIV IMPACT ASSESSMENT.


The Government of Uganda through the Ministry of Health conducts population level surveys to inform the planning for HIV activities after every five years. The last one was conducted in 2011 and this was known as the Uganda AIDS Indicator Survey(UAIS 2011). This has been very useful in improvement of the HIV interventions in this country over the past five years.

The previous round of AIDS Indicator Survey shows that HIV prevalence in the general population in Uganda increased from 6.4% in 2004/5 to 7.3% by 2011,  tallying with the 2013 HIV estimates which show that HIV prevalence stabilized around 7.4% in 2012/2013. This however seemed to undermine the fact that the country that was well known for earlier interventions that drastically reduced the prevalence in the earlier years of the epidemic is seeing a reversal. However the stagnation of HIV prevalence was partly due to the high coverage of ART program where the number of PLHIV enrolled on ART increased from about 330,000 in 2011 to about 750,896 in 2014 and the reduction in AIDS related deaths from 67,000 to 63,000 in 2010 and 2013 respectively, and down to 31,000 in 2014.

To further boost government efforts towards containing the scourge, this year, we are conducting another survey - the Uganda Population Based HIV Impact Assessment – that will measure the reach and impact of the country’s HIV prevention, care and treatment services. This nationwide household survey aims to estimate HIV incidence, prevalence, and viral load suppression among adults and children. UPHIA will also benchmark Uganda’s progress toward targets of 90% coverage in each area. This information is critical to helping Uganda chart a course to reach the UNAIDS’ 90-90-90 targets and ultimately bring the HIV epidemic under control.

The assessment exercise, which will be flagged off next month (August 2016) during a national launch in Kampala, will see up to 25 teams of trained personnel dispatched to all regions across the country. This survey will inform the next prevalence indicator and guide efforts towards reversing the HIV prevalence in the country.
Survey teams will visit approximately 13,000 randomly selected households throughout the country, who will voluntarily participate in the survey. Those who choose to participate will receive HIV counselling and testing in their home, with results returned the same day. Syphilis and hepatitis B tests will also be provided and results given on the same day.

Treatment of syphilis will be given at the household level while the HIV and Hepatitis B cases will be referred to health facilities. Children and adolescents are part of this survey. However, children will only be allowed to participate after obtaining permission from their parents or guardians.

UPHIA data will help Uganda sustain its achievements in responding to HIV, and help improve the response in the future while individuals who participate in the survey can contribute to improving health services for all Ugandans.
By combining interviews with in-home HIV counseling and testing, UPHIA can provide more accurate estimates of HIV incidence and prevalence in Uganda.

The assessment will be implemented with support from ICAP at Columbia University through the U.S. Centre for Disease Control and Prevention (CDC). The other partners include Uganda Virus Research Institute (UVRI), Uganda Bureau of Statistics, Westat and ICF Macro.

I wish to state that the success of this survey largely depends on the voluntary participation of the selected households countrywide and also on everyone encouraging and supporting the survey teams in the different enumeration areas.
It is against this background that we have engaged you as the media fraternity to partner with us in creation of awareness and play a role in engaging the different stakeholders in supporting this very noble cause.


Tuesday, 12 July 2016

UNHCR calls for open borders for possible South Sudan refugee outflows

UNHCR is calling on all armed parties to ensure safe passage for people fleeing the fighting that erupted late last week in Juba between troops loyal to President Salva Kiir and First Vice-President Riek Machar and we urge neighbouring countries to keep borders open to people seeking asylum. Inside South Sudan, some 7,000 internally displaced people have sought shelter in the UN’s bases in Juba. Providing them with food, shelter, water, hygiene and sanitation facilities will remain a critical challenge so long as the security situation remains bad. The situation of some 9,000 urban refugees is worrisome. Some refugees who spoke to UNHCR are uncertain about their security and have difficulties in getting food and water. Other refugee-hosting sites across South Sudan are reported to be calm. Meanwhile, some borders have been affected such as the Uganda-South Sudan crossing, where security is tightened on the South Sudan side. This has led to a significant decrease in the number of new arrivals coming into Uganda over the weekend. Just 95 people crossed on Saturday, dropping to 36 on Sunday, compared with a daily average of more than 200 for July. Higher levels of new arrivals are expected once the border reopens. Those that have managed to cross have reported indiscriminate attacks against civilians, with buses from Juba to the Uganda border being stopped and robbed. In western Ethiopia’s Gambella region, UNHCR has stepped up border monitoring with Ethiopia’s refugee commission. Emergency preparedness is in progress in Kenya, Sudan and other neighbouring countries in case of a major influx. There has not been any big influx at the Kenya-South Sudan border, though over the weekend UNHCR received 36 individuals from Eastern Equatoria state. We have stepped up border monitoring and await more news. For more information on this topic, please contact: In Kampala, Charlie Yaxley, yaxley@unhcr.org , +256 (0) 776 720 045 In Nairobi, Teresa Ongaro, ongaro@unhcr.org, +254 735 337 608 In Juba, Rocco Nuri, nuri@unhcr.org +256 779 663 793 In Gambella, Sulaiman Momodou, momodu@unhcr.org +251 935 978 519 In Geneva, Leo Dobbs, dobbs@unhcr.org +41 79 883 6347

Tuesday, 30 June 2015

Ssese beauty blighted by dysfunctional health system

Don’t let the tranquil, picturesque seclusion of the island district of Kalangala fool you; this home to Ssese islands, an archipelago of 84 islands, is a perfect natural beauty, but also a poster child for numerous health and system plagues associated with many far-flung districts. Seeing Lake Victoria’s waves reluctantly touch the shores and feeling the morning chill bite one’s skin is tantalizing. However, on this particular morning, hundreds of people saunter through the serpentine roads on Bugala Island to receive free medical care courtesy of a medical camp organised by Uganda Health Marketing Group (UHMG) last week. The stories from the locals about the challenges of accessing health services are striking. Robina Nakato, formerly from the island of Bubeke whose toddler died earlier this year from severe malaria, blames the death on the poor quality health care on the island. “I had earlier reported to a drug store in Bubeke and was given drugs by a ‘nurse’ since there was no doctor, but [the drugs] did not work. I cannot afford coming to Kalangala Health Centre IV all the time, because a trip costs me about Shs 40,000, which I don’t have,” the mother of two says. “My son worsened at home and a few hours after arriving at the health centre, he died.” ACCESS DELAYS There is no district hospital and Kalangala HC IV is the main referral health facility for the 64 habitable islands. The islanders have repeatedly highlighted the austerity of an inadequate transportation to access health facilities, leaving many of them to resort to the expensive and scarce private clinics or even traditional healers. “That night will forever haunt us, because I wonder, had it not been for the transport delay and earlier wrong diagnosis, would my son be alive?” Nakato forlornly says. According to Willy Lugoloobi, the Kalangala district chairman, Bubeke and Mazinga islands are the hardest to reach. It will cost a person 80 litres of fuel and four litres of oil to travel from Bubeke to Kalangala HCIV. For those from Mazinga Island, the furthest from Kalangala town council, it takes 100 litres of fuel and five litres of oil. Each litre of fuel costs Shs 5000 in these parts. “In Kalangala, a walkable distance is talked of in terms of a swimmable distance. It is not only a hard-to-reach district but also a hard-to-stay in. About Shs 600,000 for primary health care is channelled in per quarter but even accessing that money from the bank is hard. In Mazinga, you have to use eight litres of fuel to reach the bank,” Lugoloobi says. All the islands are served by only 15 health centres, two thirds of which are located on Bugala, Kalangala district’s biggest and administrative island. Further referrals to Entebbe hospital or Masaka regional referral hospital are facilitated by the MV Kalangala ferry that costs Shs 15,000 per head from Lutoboka to Nakiwogo in Entebbe, and MV Pearl that docks at Bukakata, respectively. Deeply concerned for the wellbeing of their other children, Nakato and her family moved to Bugala last year. Unlike Nakato who could afford moving nearer to the health facility, thousands remain stranded on smaller islands meaning that delays in accessing health care services is costing lives and hampering the right to health. According to the 1995 Uganda Constitution, Objective XIV (b), the state shall ensure that all Ugandans enjoy the rights, opportunities and access to health services. However, the realisation of this access is still a far cry for the locals in Kalangala. According to the district’s statistics, only 17 per cent of expectant women deliver in health facilities. Sarah Subo, a health educator with the district for 15 years, says majority of the women depend on traditional birth attendants. MORE DEPRESSION Although health worker deployment is at 80 per cent within the district, Lugoloobi says that harsh working conditions are forcing medical workers out. “Teachers are now forced to share their accommodation with medical workers, because medics have nowhere to sleep,” he agonised. Moreover, HIV prevalence remains high at 25 percent which implies that 25 of every 100 people are infected. Subo attributes the high prevalence to the falling condom use in the face of ever increasing commercial sex associated with fishing communities. “Unprotected sex costs Shs 20,000 and above, whereas protected sex is negotiable from about Shs 5000. Having more than eight sexual partners and swapping them is also common,” Subo explains, adding that the vice is spreading to adolescents too. The high prevalence is also brought on by drug stock outs in some months. To deal with these challenges, Prof George Kirya, a founder member of UHMG says it (UHMG) organises annual health camps in the district, bringing drugs, HIV testing, cancer screening, immunisation and health awareness closer to the locals. However, Lugoloobi says, all the health problems cannot be met in a health camp. “We need a district hospital and more health centres, because each of the seven sub counties is supposed to have a Health centre III. We appreciate the camp efforts but if one gets sick after, they are met with the familiar challenges,” he said. NEW PLEDGES Sarah Opendi, the state minister of health in charge of primary health care pledged to give the district two motorised boats to ease health workers’ movement among the islands. Their delivery is expected in August this year. “Government is also going to give the district priority status and establish maternity wards to reduce on maternal deaths,” she told residents during the health camp. Opendi, however, urged them to observe personal hygiene and safe practices to avoid diseases such as cholera. At least 1000 women, men and children attended the camp.

Saturday, 14 March 2015

New cancer unit lights up patients

Each day, about 200 people report to the Uganda Cancer Institute (UCI) in Mulago for treatment, checkups and counseling about the devastating malignancy. Some of them travel miles from the Democratic Republic of Congo (DRC), Burundi and Tanzania because UCI is the only national and regional free cancer referral centre.
Outside the outpatient department, tens of patients try to find sits, floor space and tree shades to rest and wait because wards are full. When the sun sets, patients who cannot afford transport fare back home saunter into the wards to sleep. Christine Namulindwa, the institute’s publicist, says the prohibitive cost of cancer treatment in private facilities has led many to seek free treatment at the institute. The high cost of equipment and drugs explain the exorbitant cost of treatment.
“The cheapest cancer treatment is about Shs 14 million and majority of the patients cannot afford it, which explains the overcrowding here. However, we are also met with the challenge of limited skilled personnel as there are only 12 oncologists,” Namulindwa says.
Children afflicted with cancer find rest-Photo Credit/Nicholas Bamulanzeki

In the past few years, UCI has reported a spike in cancer incidence, particularly infection related cancers such as Kaposi Sarcoma, sending a wakeup call to government. Although there is no nationwide data, estimates obtained from UCI’s registry indicate that some 300,000 Ugandans develop invasive (advanced stage) cancers and over 10,000 of these die annually.

NEW PREMISES
In 2011, government invested Shs 10.4 billion to construct a new, modern cancer unit. Currently, some of the wards on this six-floor unit are up and running. For now, mainly children, patients admitted to the private wing and those going to be operated are using the facility. Majority of patients are still using the old block as the new block is short of medical equipment.  
The new cancer block-Photo credit/Nicholas Bamulanzeki

Inside the children’s ward on level four, hued caricatures painted across the walls are a fresh face to the children’s treatment. Accordingly, these play a role in keeping the little ones in high spirits. Six year old Jordan Kibirige from Mukono was admitted here one week ago.
He is battling Burkitt’s lymphoma, a potentially fatal cancer that has left him with a painful swelling on the left side of his face. The lymphoma, associated with malaria, is known to grow rapidly such that the tumours double their size in five days.
“So far, we have been able to get quick treatment and bed space at this new facility. I hope my boy will soon recover,” Kibirige’s mother forlornly says.
At least one doctor and nurses are on duty here throughout the day, a sign of relief to the over 20 patients here.
So far the journey is comfortable; clean toilets, lifts, regular electric power, piped water and free lunch. The theatre, on level two, is operational and Namulindwa says it has greatly reduced congestion at Mulago hospital’s general theatre. The building also has a mortuary, intensive care unit, private wing and an imaging and nuclear medicine department.
Inside the children's ward

However, Namulindwa expresses fear that with the swelling number of patients, this facility will soon be overwhelmed.
“The new centre is expected to accommodate 100 patients but we’ll be seeing more than these,” she said.
The new facility will officially open mid this year.

MORE DEVELOPMENTS
A comprehensive state-of-the-art research, training and outpatient cancer centre is currently in the final stages of construction. The Hutchinson Cancer Research Institute- Uganda sits on 25,000 square feet and will include an outpatient clinic, chemotherapy infusion rooms, research laboratories, molecular diagnostic labs, a training center and data centre among others.
This facility seeks to ensure the availability of medical care, overcome the social and economic barriers to completing treatment and improve capacity of the medical infrastructure to diagnose and care for patients. With the new premises, it is hoped that the five-year survival rate of cancers such as leukemia which is less than 40 per cent will be improved.
The centre, whose construction began in April 2013, is slated to officially open in May this year. It is supported in part by the United States Agency for International Development, American Schools and Hospitals Abroad Programme.
Namulindwa also told The Observer that plans are underway to construct a Radiotherapy and Nuclear Medicine Centre.
In spite of these developments, challenges of limited beds and equipment, medical personnel brain drain and forbiddingly expensive drugs are rife.
“Diagnosis equipment for examining biopsies is only available at Mulago Referral hospital and because of the limited number of pathologists, results take up to two weeks to return,” Margaret Okello, a volunteer counselor at UCI, notes adding that there is only one radiotherapy machine in the entire referral hospital.
Moreover, because of the limited number of oncology personnel, nurses have had to be trained on the job in order to administer drugs.
Okello and Namulindwa urge government to subsidize pharmaceutical companies that supply drugs in order to make them more affordable and available.

“We also appeal to government to adequately remunerate skilled personnel and invest in the purchase of modern equipment such as a magnetic resonance imaging machine,” Namulindwa says. 

This article first appeared in The Observer.

Sunday, 31 August 2014

TB drugs: poor countries hanging by the thread

Julius Kiiza, 26, was like many youths his age a few years back. He loved to hang out and live a good life. Never in his wildest dreams did he think he was developing a virulent form of Tuberculosis – the multi drug resistant TB (MDR-TB).
I met him at Hoima regional referral hospital TB ward. As he motioned towards me, it was as if his legs would snap under the weight of his body.
Kiiza, a father of four, was diagnosed with MDR-TB on November 28, 2013. Prior to this, Kiiza was already grappling with HIV which was discovered in 2011.
He was to later develop a wracking cough, characterized with chest pain.
“I would lose breath especially at night because of chest congestion,” he said.
Kiiza was diagnosed with TB and was started on the regular eight month drug regimen. Five months down the road Kiiza was found to have MDR-TB.
MDR-TB occurs when bacteria do not respond to Isoniazid and Rifampicin, the two most powerful, first-line anti-TB drugs.

Because of Kiiza’s co-infection (HIV and TB), he swallows at least 20 pills a day and he will be receiving an anti TB injection daily for six months.
 NEW RESEARCH ELUDES LDCs
While identifying those with the active disease will provide a long-term public health benefit, Moses Mulumba, a patent lawyer says that without new, simple and affordable treatments for MDR-TB, this is impossible.
“If pharmaceuticals developed one tablet a day for TB, this would mean reduced pill burden and greater adherence. However, such developments for the developing world are deficient due to the lack of return on investment opportunities for pharmaceutical companies,” says Mulumba, the executive director of Center for Health, Human Rights and Development (CEHURD).  
Most recently, Britain/Sweden pharmaceutical, AstraZeneca announced it was pulling out of all early stages of research and development for malaria, TB and neglected tropical diseases to instead focus on cancer, diabetes and hypertension.
Welcome to the world of intellectual property (IP), where giant pharmaceuticals determine drug availability and pricing.
Prices of drugs vary depending on whether the drug is under patent – 20-year protection by the manufacturer – or generic, where the patent has expired.
In the private sector market, the brand/patented version of Linezolid, an MDR-TB treatment drug, costs $65 (approximately Shs 166,400) for a daily pill. For a patient taking a pill a day for two years, this amounts to over $49,000 (over 125m). It is produced by Pfizer, an American pharmaceutical corporation.
Generic versions of the drug, produced by Hetero, an Indian pharmaceutical company, cost of $8 (Shs 20,000) per pill.
When asked whether he would have afforded Linezolid had it not been provided freely, Kiiza laughed sarcastically: “I think I would have died a long time ago because I don’t have a cent!”
Because majority of Ugandans still survive on less than $1 (Shs 2,560) a day, Uganda receives TB drugs through aid.
The case of ARVs provides a dramatic illustration of the global impact of Indian drug firms.
In 2001, Indian drug company Cipla, introduced first line treatment for HIV at $ 350 (Shs 896,000) per person per year, a stunning offer at the time.
Other Indian firms followed Cipla’s model and today, 80 per cent of people living with HIV who are on treatment in developing countries rely on Indian generic drugs. 

TRADING AWAY LIVES
Uganda being a member of the World Trade Organization (WTO) is under obligation to develop rules that comply with WTO guidelines. Among these is the Trade Related Aspects of Intellectual Property (TRIPS) agreement requiring all members to standardize minimum standards of IP, including patents for pharmaceuticals.
IP rights give the creator an exclusive right over the use of his or her creations for a certain period of time, such as 20 years, for a scientific innovation like medicine.
The pharmaceutical industry in developed countries strongly depends on the patent system in order to recoup research and development costs.
“TRIPS sustain a regime of private monopoly rights which impedes access to essential medicines because of prohibitive prices. It also delays production and market entry of generics because producers will have to wait 20 years for a patent to expire,” Mulumba explains.
Moreover, countries such as India and Brazil where generics are produced now grant medicines patents in order to comply with their obligations as WTO members. New drugs are already patented in these countries meaning that production of affordable generics is now restricted.
Such a restriction led Cipla to establish Quality Chemicals Limited in Uganda because that law does not hold for LDCs.
Under TRIPS, LDCs are supposed to enforce patents on all medicines by 2021. Tentatively, this means the end of all generic drugs.
In response to the TRIPS agreement, WTO delegates issued the Doha declaration on November 14, 2001 which exempts LDCs from implementing patent law for pharmaceuticals until January 1, 2016. This was extended to 2021 last year.

ENFORCING PATENTS IN UGANDA
To guarantee intellectual property rights to innovators, parliament this year passed the Industrial Properties Act. It spells out protection for products and processes in all fields of technology, including medicine.
Mulumba forecasts that the law will only work if there is government commitment to invest in research and development, develop human capacity and offer attractive incentives such as tax holidays to innovators.
“The law integrates flexibilities such as the bolar provision which enables researchers’ reverse-engineer drugs even when the patent on it has not yet expired. But all the seven plants we have are not doing research because of high production costs,” he says.
Another policy is the Anti-Counterfeit Goods law which prohibits the manufacture, trade and release of fake goods on to the market. Contentious, however, is the fact that it regards generics as counterfeits.
 “This is part of a global agenda to keep developing countries from importing from third parties like India and Brazil where the cost of production is much cheaper. All these things are happening because we are a disorganized lot. We Africans are doomed unless we wake up!” says Edgar Tabaro, a patent lawyer with Karuhanga, Tabaro and Associates.

SOLUTIONS TO A GLOBAL CRISIS
In 2000, the UN Security Council declared HIV a global security issue and resolved to establish a Global Fund (GF). GF is the biggest financer for HIV and TB programmes in Uganda, having channeled at least $ 200m over the years.
“In October, Uganda is sending the GF another proposal for HIV/TB funding to enable us scale up prevention and treatment efforts,” Prof Vinand Nantulya, chairman Uganda Aids Commission said.
Uganda is also a member of WHO’s Global Drug Facility (GDF), the largest supplier of quality TB treatments. Nantulya says it is through this that the country procures TB medicines and innovative tools such as the GeneXpert at reduced prices.
“Uganda needs to develop collaborative research so that our scientists can catch up with others in the developed world and partnerships such as the Global Alliance for TB drug development should be more actively supported to allow for the development of drugs that are free of patent restriction,” Tabaro urges.
Currently, 11 TB vaccines are in clinical trials worldwide. WHO estimates that the earliest a vaccine could be licensed is 2020. BCG (Bacille Calmette Guerin) vaccine remains the only vaccine against TB in general use.

This story was supported by the African Center for Media Excellence. 

Tuesday, 5 August 2014

Better TB management urgently needed

I had heard about Tuberculosis (TB) and the wreckage it causes in a patient’s life just in the passing, until I set out to document issues hindering drug access.
The dismal condition of a patient I found at Bulondo Health Centre III in Wakiso district exceeded my saddest expectations.
Fred Musoke’s lips were chapped, dry and red, bones almost visible and his skin dark as ebony.
He tossed and turned, seeking comfort, coughing and spitting into his lesu.
Death, he said, would be a reprieve.
“I feel feverish all the time and do not have appetite. The woman that I wanted to marry left me about two months ago because of this sickness,” he muttered from behind a dark green mask covering his mouth and nose. He keeps the mask on to avoid spreading the TB to others. Before I could talk to him, I was handed one too.

Before getting TB, Musoke, 31, was a market vendor selling second hand clothes. Then five months ago he was diagnosed with TB.
“I was admitted two weeks ago after becoming so ill one weekend that I could not walk,” he said.
Because Musoke has HIV, he is no stranger to the health centre. It is here that he has been getting ARVs. 
However, his struggle is further complicated by inadequate drugs at the facility.
“Many of our health facilities do not have some of the most required drugs such as Ethambutol, Isoniazid and Rifampicin needed to treat regular TB and also Septrin which is necessary in fighting opportunistic infections like TB in people with HIV,” says Expedit Mwambazi, Wakiso district’s TB focal person
The centre’s laboratory room was crawling with spiders and wasps instead of diagnostic equipment. It has been so for over five years according to one of the health workers. 
Many health centres do not have TB units, which has perpetuated the mixture of TB patients with other patients. The World Health Organization (WHO) warns that people with TB can infect up to 15 other people through close contact.
TB remains the biggest killer of people living with HIV, causing nearly 50 per cent of deaths. Primah Kazoora, a TB survivor, says malnutrition, living in slums and poorly ventilated houses also accelerate the development of TB.
THE LETHAL ANNIHILATOR
Tuberculosis is one of the deadliest and most disabling diseases. It is an airborne disease caused by a type of bacterium; mycobacterium tuberculosis, transmitted by being in proximity to coughing, talking or sneezing patients. 
If not treated promptly and consistently, says Dr Alphonse Okwera the head of Mulago hospital’s TB treatment centre, it weakens the patient, damages the lungs and may spread throughout the body.
In its advanced stages, the sputum comes with blood.
TB affected lungs/Photo-Courtesy

TB kills some 4,700 Ugandans every year.
In its 2013 report, WHO noted that of the 8.6 million people that fell ill with TB in 2012, 1.3 million died. At least 95 per cent of these deaths were recorded in middle and low income countries such as Uganda, Ethiopia and Swaziland.
“In 2012, an estimated 530,000 children became ill with TB and 74,000 HIV-negative children died of TB. At any given moment, 12 million people globally are suffering from an active infection,” reads the report.

TB kills someone approximately every 25 seconds and an estimated nine million new cases develop each year.

The WHO report ranks Uganda 18th out of 22 high-burden countries that account for 80 percent of new TB infections worldwide. According to Ministry of Health and the National TB and Leprosy Programme (NTLP), there were approximately 49,000 new TB cases in Uganda in 2011. 

“The high burden of the TB disease is mainly in the urban and peri-urban centres, with Kampala accounting for 7,800 cases, Wakiso 1,300 cases and other regional towns account for between 1,300 – 1,600 cases each,” says Dorothy Namutamba, the program officer at the International Community of Women Living with HIV/Aids, Eastern Africa (ICWEA).

Although its burden is spread across all age groups, TB exacts its greatest toll on individuals during their most productive years, from ages 15 to 44.
CHALLENGES IN THE TB COMBAT
Uganda in 2000 pledged, as part of the Millennium Development Goals (MDGs), to halve TB prevalence and deaths by 2015. But despite setting up over 1,200 diagnostic centers nationwide it is still far from these goals.
Namutamba says one of the major setbacks is lack of priority and limited information about TB in communities.
“Unlike HIV which has gained ground through community sensitizations and literacy programmes implemented by government and the civil society efforts, TB has been left to the laboratories and the health care providers,” she says.
In an assessment study by ICWEA on the availability and accessibility of TB/HIV services in Kampala, Wakiso, Mityana and Mubende districts between 2010 and 2012, majority of the interviewees showed low knowledge on TB .
“When a person develops active TB, the symptoms including cough, fever, night sweats, weight loss and blood stained sputum, may be mild for many months. This may lead to delays in seeking care,” says Dr Okwera.
Another challenge is the long duration of treatment, lasting at least eight months. 

RISE OF A SUPERBUG

Because of the seemingly long duration, many patients abandon the drugs. 
“Only 78 per cent of those with the disease undergo successful treatment and the other fraction are those that die, fail on treatment and those for whom follow up is lost,” says Dr Frank Mugabe, the acting program manager, NTLP.
Lack of drug adherence has urshered in new drug resistant forms of the bacterium, spreading a new phenomenon of Multi Drug Resistant TB (MDR-TB).
MDR-TB is a form of TB caused by bacteria that do not respond to, at least, Isoniazid and Rifampicin, the two most powerful, first-line anti-TB drugs.
Currently, the two year drug regimen for MDR-TB costs $3,000 compared to $10 to treat regular TB.
“[Comprising] about 20 pills a day and painful injections for six months, MDR-TB treatment is difficult to adhere to. Even if patients adhere, half are likely to die from this type of TB,” says Dennis Kibira, a pharmacist and deputy director of the Coalition for Health Promotion and Social Development (HEPS-Uganda).
In a move to nip resistance in the bud, Dr Mugabe says the country has improved its ability to test for drug-resistant TB by introducing the GeneXpert, a rapid testing machine that can diagnose TB in sputum samples in less than two hours.

GeneXpert machine/Photo-Courtesy

Nevertheless, there are only 14 treatment sites in the country. The ICWEA survey notes that Mubende hospital at the end of March 2013, had five patients who had been confirmed with MDR TB but sent them home because of the hospital did not have drugs to treat them.
“We need a shorter treatment option to transform TB treatment from an agonizing ordeal, to a shorter, more tolerable, more effective and more affordable treatment course,” urges Kibira.

In our second part, we shall examine how patent rights are prohibiting access to new drugs and diagnostic technology in Uganda. 

This story was supported by the African Centre for Media Excellence.

Saturday, 19 July 2014

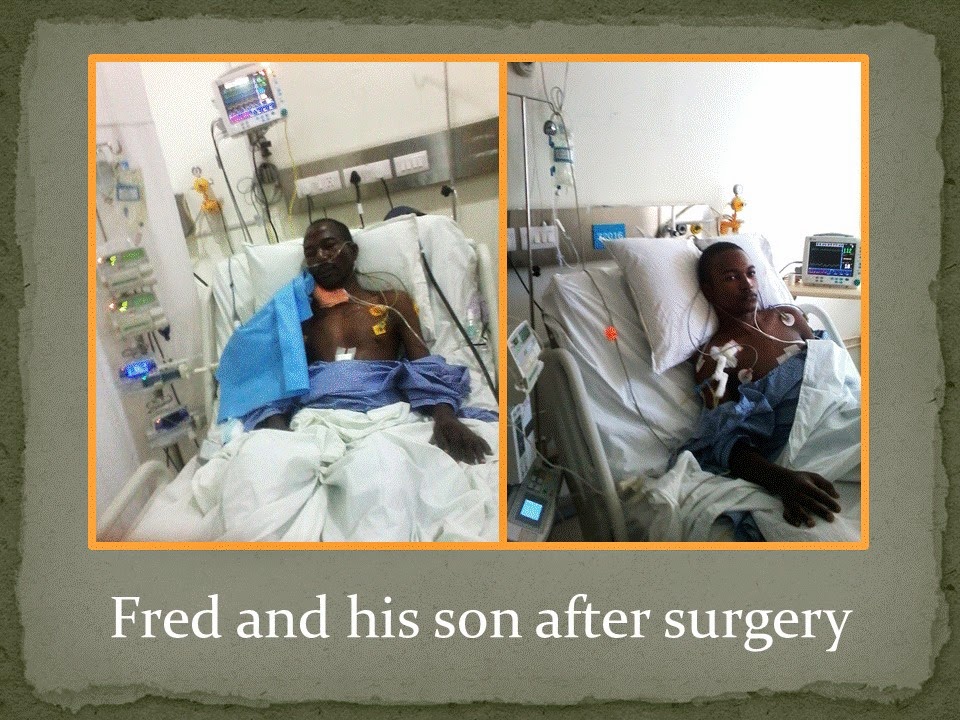
Kiyingi cheats death with son’s liver

Staying active and engaging in sports has been Fredrick Kiyingi’s lifestyle since childhood.
However, as he grew older, his daily life was affected so much that by 30, he could not partake in any physical activity.
He was 37 years old when a medical examination by Prof Michael Kawooya, a senior radiologist at Mengo hospital revealed that his gall bladder was releasing toxins into the liver. It was also on the verge of rupturing. 
Kiyingi, now 47, was born with a liver problem medically termed as choledochal cyst.
Dr David Ndawula, the medical director of Kampala Family Clinic says a choledochal cyst occurs when the bile duct, a vessel that leads bile to the intestines from the liver, is structured abnormally.
“This causes bile to accumulate in the duct resulting in duct damage and formation of a cyst (fluid-filled sac),” Dr Ndawula explains.  
He says that a liver transplant becomes necessary when the liver has been damaged to the extent that it cannot perform its normal functions. This is known as liver failure.
The liver is one of the largest organs in the body. It produces bile necessary in digestion of fats, makes agents needed for blood clotting, removes toxins from the blood stream and controls blood sugars, among other functions. 
“Although liver failure can be managed by medication, this can sustain one in good health for a short while. A liver transplant is the only cure for liver failure,” he says.

RUNNING OUT OF STEAM
In 2001, an acute pain on the right side of his abdomen became a bedfellow. It caused him severe loss of appetite and nausea.
“To keep the pain at bay, I devotedly relied on drugs meant to cure peptic ulcers because doctors suspected I was suffering from these,” said Kiyingi, the safety and security coordinator of US Peace Corps - Uganda.
He used the drugs between 2002 and 2005.
But by May 2005, Kiyingi was starting to feel much more tired. His body darkened and thinned so much that he suspected HIV.
“Once, I went to Kampala family clinic in Nsambya to buy pain killers and told Dr Ndawula that I had HIV. He told me to open my mouth and stick my tongue out and hinted on the possibility of a gall bladder and liver complication,” the soft spoken father of two said.
He was referred to Prof Kawooya who treated him immediately, noticing that the gall bladder was about to rupture.
Ruptures are most commonly caused by an inflammation of the gallbladder. The most common causes are gall stones. The initial symptom of a gallbladder rupture is a sudden onset of sharp or severe pain.
Kiyingi was later admitted at Case Clinic.
“I stayed at Case for three months and while here, I had jaundice, fever, more pain and my skin got darker,” he recalls.
Ndawula says jaundice is caused by the liver’s failure to remove bilirubin, a brownish yellow substance found in bile.
Kiyingi was operated upon and his gall bladder, plagued with gall stones was removed together with a fraction of the affected liver.
Dr Ndawula says a portion of a liver can be removed because of the liver’s unique ability to regenerate. It is the only organ in the body with this capability.

WORSE BECOMES WORST
Just two weeks after the first operation, his stomach started swelling tremendously because the improvised plastic bile duct was misdirected.
“Immediately, I was rushed to Mengo hospital in an ambulance and about three litres of dark green bile were drained from my body,” he reminisces.
A metallic tube was inserted into his body to drain the excess bile and liver function tests showed that his liver had completely deteriorated. He was thus linked to Prof Godfrey Lule, a consultant physician and gastroenterologist at Nairobi hospital.
To raise money needed for treatment in Nairobi, Kiyingi sold all his six cars and ended a transaction meant to purchase a house.
At Nairobi hospital, a magnetic resonance imaging (MRI) test revealed that Kiyingi’s liver was completely rotten. He was now referred to Apollo hospital in India for further treatment.
He arrived at the hospital on December 24, 2013 and examinations revealed that he had liver cirrhosis –an abnormal liver condition in which there is irreversible scarring of the liver.
 “The doctors here told me that I had only six months to live unless I underwent a transplant for which I needed $60,000 and a donor,” he says.
Fortunately his son, Laurin Baalu, 18, was willing to part with a portion of his liver.


THE FINAL STRAW
He was operated upon on March 12 at the Health Care Global Enterprises in Bangalore-India. He remained in the intensive care unit for two weeks and was discharged on April 17.
Although Kiyingi has been down the hatches, he is one of the few lucky ones; he is on the road to recovery. His chocolate skin complexion is back and he has resumed work.

However, he is now on life medication and needs $ 16,385 (about Shs 42m) to clear HCG’s hospital bill

For contribution, Kiyingi can be reached on 0776578667 or direct account deposits may be made to A/C no. 1100035091-Housing Finance Bank or 6004149376-Barclays Bank.